
Last updated on
Oct 2, 2026

Centura Health CHCR-004 2012-2026 free printable template
pdfFiller is not affiliated with any government organization
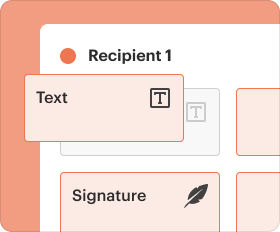
Fill out
Complete the form online in a simple drag-and-drop editor.
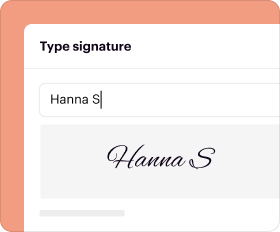
eSign
Add your legally binding signature or send the form for signing.
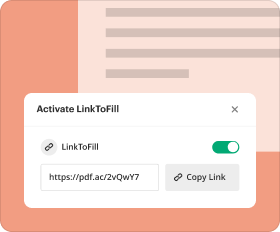
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Centura Health CHCR-004
The Patient Authorization to Disclose Protected Health Information is a legal document used by patients to authorize the release of their protected health information to specific entities.
pdfFiller scores top ratings on review platforms




It is really easy to use and had the form I needed. Very pleased!
Love this software. It is user friendly and easy to navigate.
Who needs Centura Health CHCR-004?
Explore how professionals across industries use pdfFiller.

Centura Health CHCR-004 is needed by:
-
Patients seeking to share their health information
-
Parents or legal guardians managing a minor's health records
-
Healthcare providers requiring access to patient data
-
Insurance companies needing verification of medical history
-
Legal representatives involved in medical cases
Comprehensive Guide to Centura Health CHCR-004
What is the Patient Authorization to Disclose Protected Health Information?
The Patient Authorization to Disclose Protected Health Information is a vital document that enables individuals to authorize the release of their sensitive health data to designated entities. Its primary intention is to ensure that patients have control over who accesses their protected health information (PHI). PHI encompasses a wide range of data, including medical histories, treatment details, and billing information.
Understanding this patient authorization form is essential for maintaining patient privacy and ensuring that they can share information necessary for their care. The form serves as a legal document that protects both patients and healthcare providers when disclosing personal medical information.
Purpose and Benefits of the Patient Authorization to Disclose Protected Health Information
This authorization form plays a crucial role in healthcare by facilitating the seamless sharing of medical records, which is essential for continuity of care. By allowing healthcare providers to exchange medical information, patients can benefit from coordinated treatment across different providers.
Moreover, this document reinforces patient rights regarding their health information. Patients are empowered to decide when and how their medical data is shared, ensuring a level of transparency in their healthcare experiences.
Key Features of the Patient Authorization to Disclose Protected Health Information
Understanding the specific attributes of the Patient Authorization form is essential for accurate completion. Key features include:
-
Patient's name and date of birth
-
Last four digits of the Social Security number
-
Explicit purpose for disclosure
-
Expiration date of the authorization
-
Required signatures for validation
These elements are critical to ensure the form is completed correctly, and they help define the parameters under which PHI can be shared.
Who Needs the Patient Authorization to Disclose Protected Health Information?
Various individuals may need to complete this authorization form, including patients themselves, parents, or legal guardians. It is particularly important in scenarios involving transitions between healthcare providers or other situations where sensitive medical information is shared.
Common use cases include:
-
Patients transferring to a new doctor
-
Parents seeking access to their child's medical records
-
Guardians requiring information for legal or care purposes
In each case, the authorization ensures that all parties comply with healthcare privacy regulations.
How to Fill Out the Patient Authorization to Disclose Protected Health Information Online (Step-by-Step)
Filling out the Patient Authorization form online using pdfFiller is straightforward. Follow these steps for accuracy:
-
Access the pdfFiller platform from any web browser.
-
Search for the Patient Authorization form template.
-
Fill in the necessary fields, including personal information and disclosure details.
-
Review the completed form for errors.
-
Submit the form electronically or prepare for printing.
Each field must be completed carefully to avoid delays in processing the authorization.
Review and Validation Checklist for the Patient Authorization Form
Before submitting the Patient Authorization form, it's crucial to double-check all information to prevent common issues such as:
-
Missing signatures or initials
-
Incorrect personal information
-
Omitted purpose of disclosure
Following a thorough review checklist helps validate the form’s accuracy, ensuring swift processing and compliance with healthcare requirements.
Submission Methods and Where to Submit the Patient Authorization to Disclose Protected Health Information
There are several methods available for submitting the Patient Authorization form. Users can choose from:
-
Online submission via a secure platform
-
Mailing the form to the specified healthcare provider
-
Faxing directly to a designated department
It's essential to be aware of any state-specific requirements or particular organizations to which the authorization must be submitted, especially in Colorado.
Security and Compliance for the Patient Authorization to Disclose Protected Health Information
Handling sensitive information is paramount in healthcare. pdfFiller implements robust security measures, including 256-bit encryption, ensuring compliance with HIPAA regulations. This commitment to data protection guarantees that patient health information remains confidential and secure throughout the process.
Using a trusted platform like pdfFiller alleviates concerns regarding data breaches or unauthorized access, providing peace of mind to users.
Common Rejection Reasons and Solutions for the Patient Authorization Form
Submitting the Patient Authorization form can occasionally lead to rejection due to specific pitfalls. Common reasons include:
-
Incomplete fields or missing signatures
-
Not specifying the purpose of disclosure
To address these issues effectively, users should carefully review their forms before submission and take the necessary steps to amend any discrepancies. This proactive approach can significantly reduce potential delays.
How to Get Started with pdfFiller to Complete Your Patient Authorization Form
Getting started with pdfFiller for filling out your Patient Authorization form is easy. The platform offers user-friendly features that enhance the form completion process, allowing users to edit and manage documents effortlessly in a cloud-based environment.
Utilizing pdfFiller not only streamlines the form-filling experience but also ensures the efficient and secure handling of health information, empowering users to manage their healthcare needs effectively.
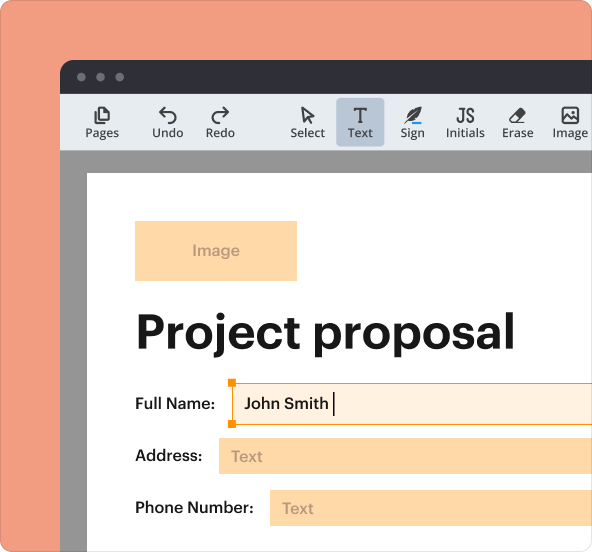
How to fill out the Centura Health CHCR-004
-
1.To access the form, go to pdfFiller and log into your account. Search for 'Patient Authorization to Disclose Protected Health Information' in the document search bar.
-
2.Once you find the form, click on it to open. This will redirect you to the editing interface, where all fillable fields will be visible.
-
3.Before filling out the form, gather all necessary information such as the patient's full name, date of birth, last four digits of their Social Security number, and the reasons for the information disclosure.
-
4.Begin typing into the designated fields. Use the tab key to navigate between fields efficiently. Ensure you fill in all required fields marked clearly on the form.
-
5.Review your entries carefully. Double-check names, numbers, and the types of information authorized for release to prevent errors.
-
6.Once all fields are completed and verified, look for the signature section. Both the patient and the parent or legal guardian need to sign where indicated.
-
7.After signing, explore the options for saving your document. You can download a PDF version, save it to your pdfFiller account, or choose to submit it directly to the relevant parties using the platform.
What information do I need to fill this form?
You will need the patient's full name, date of birth, the last four digits of their Social Security number, and other details such as their address. Additionally, specify the recipients of the health information and the purpose of disclosure.
Do I need to notarize this form?
No, the Patient Authorization to Disclose Protected Health Information does not require notarization, but it does require the patient's signature and possibly a signature from a parent or legal guardian.
How long is the authorization valid?
The form allows you to specify an expiration date. Typically, this can be set for a period ranging from several months to several years, depending on the purpose of the disclosure.
How do I submit the completed form?
You can submit the completed form via mail to the healthcare provider or organization specified in the authorization. You may also submit it electronically if that option is available.
What are common mistakes to avoid when filling out this form?
Common mistakes include missing signatures, incorrect Social Security numbers, and not specifying the purpose or recipient of the disclosures. Always review the form before submission.
Is there a deadline for submitting this form?
While there is no universal deadline for submitting this authorization form, it is essential to submit it in a timely manner to ensure your healthcare providers can access your information without delays.
Who can I contact if I have questions about this form?
For questions regarding the form, you should contact your healthcare provider’s office or the organization to which you are sending the form. They can provide specific guidance and support.
Centura Health CHCR-004 Form Versions
Related Content
Related Forms


If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.